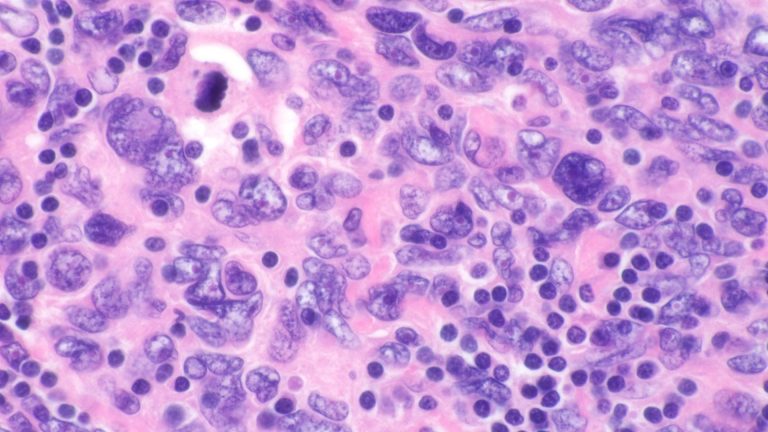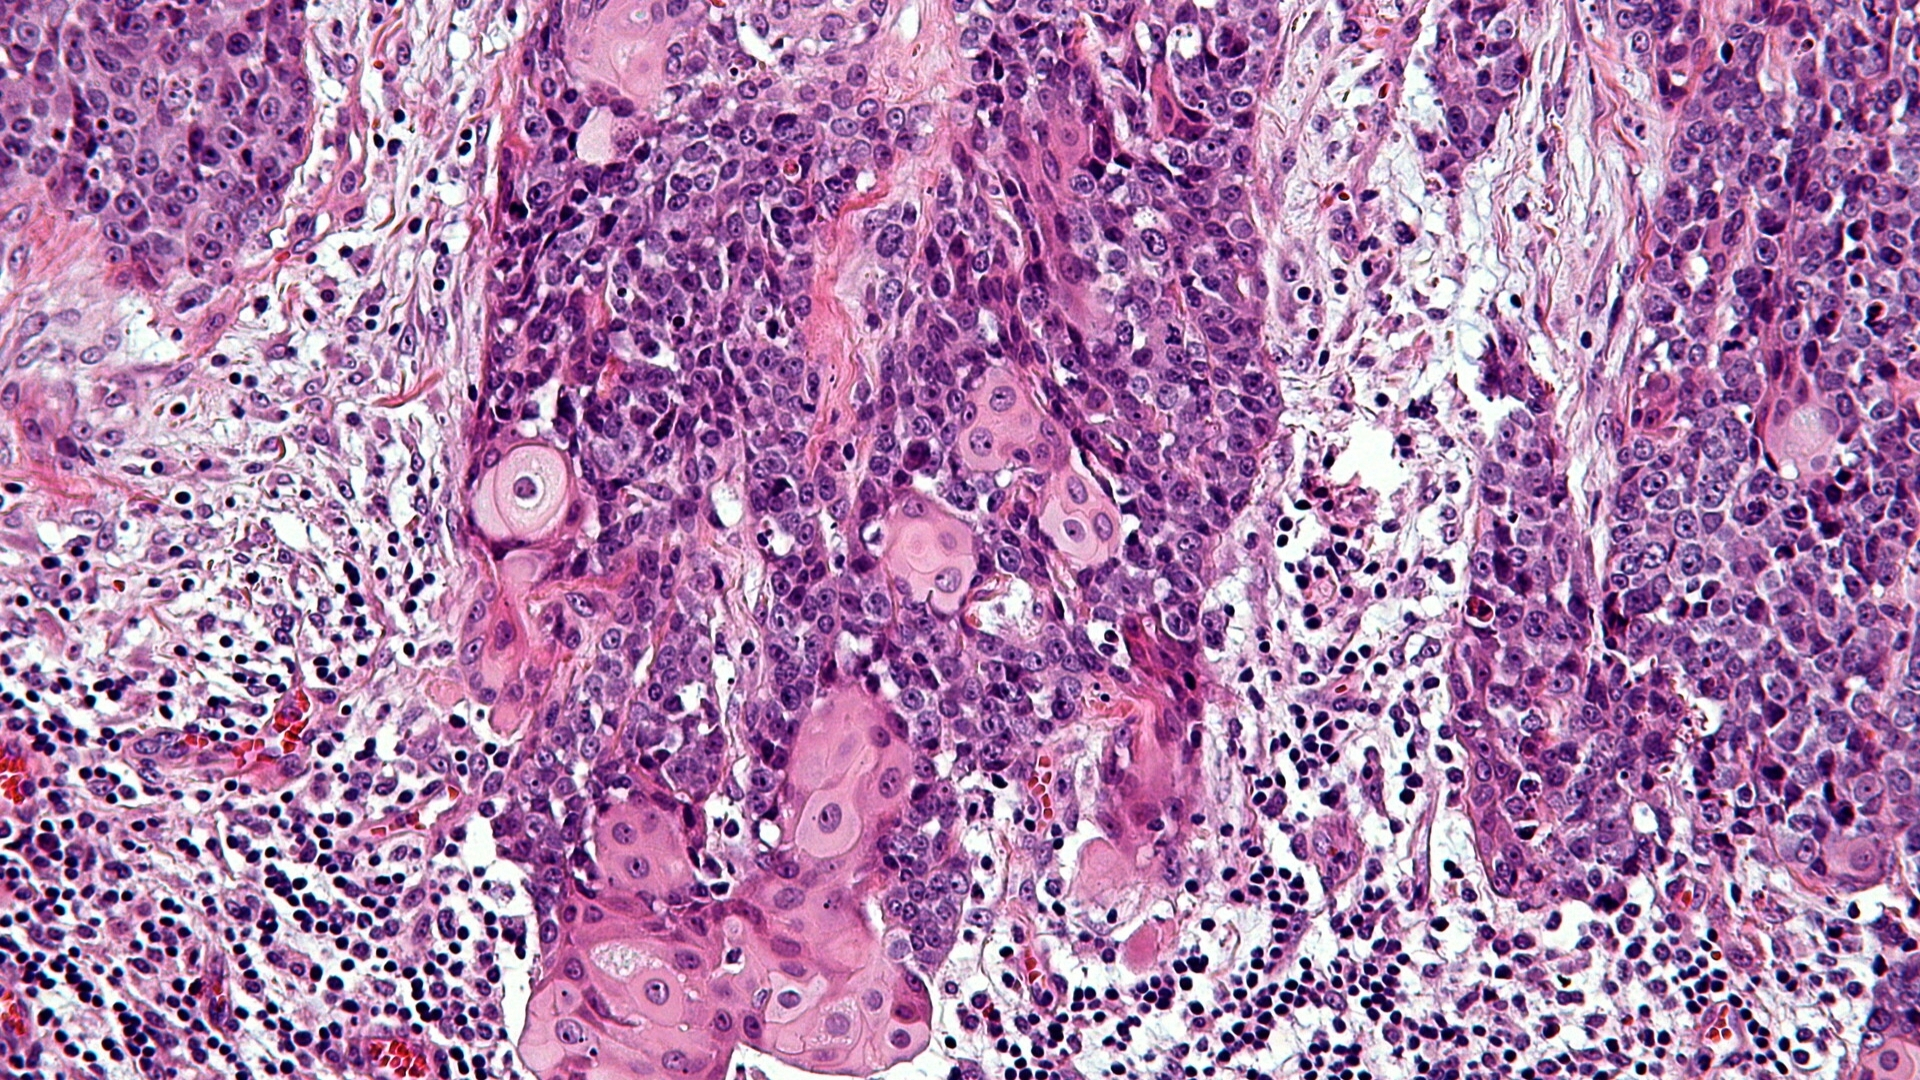
Midline Tract Carcinoma (NUT Carcinoma) is an extremely rare yet aggressive form of cancer characterized by specific genetic mutations. Typically arising along the midline structures of the body—such as lungs, mediastinum, nasal cavities, or salivary glands—this malignancy is distinguished by the rearrangement of the nuclear protein in the testis (NUTM1) gene located on chromosome 15. The resulting genetic alteration fosters abnormal cell proliferation and rapid tumor growth.
What Is Midline Tract Carcinoma (NUT Carcinoma)?
One defining hallmark of Midline Tract Carcinoma (NUT Carcinoma) is its dramatically accelerated glucose metabolism—a process known as the Warburg Effect. This means that the cancer cells in NUT Carcinoma consume glucose up to 200 times faster than normal cells. Such extreme dependence on glucose metabolism opens novel therapeutic avenues, exploiting metabolic vulnerabilities to strategically target cancer cells without harming healthy ones.
Understanding the Biological Basis of Midline Tract Carcinoma (NUT Carcinoma)
In recent years, groundbreaking research, endorsed by renowned Nobel laureates such as Professor James P. Allison and Dr. Gregg Semenza, has illuminated the molecular landscape of NUT Carcinoma. Manifestations of this cancer result predominantly from chromosomal translocations that fuse NUTM1 gene with genes such as BRD4 or BRD3, causing rapid and uncontrollable cellular division.
- Typically originates along body midline regions.
- Exhibits aggressive tumor growth patterns.
- Marked by genetic translocations involving the NUT gene.
- Strong dependence on enhanced glucose uptake for survival (Warburg Effect).
In Hong Kong and broader Asia, cases of NUT Carcinoma remain underreported due to challenges in accurate diagnosis and misclassification. Globally, the number of confirmed diagnoses remains limited, with fewer than 100 cases reported annually. However, heightened awareness and advances in genetic testing are leading to increased detection, providing hope for timely diagnosis and effective treatment.
Prevalence and Affected Population in Asia and Hong Kong
While precise prevalence rates are challenging due to rarity, global oncology reports estimate fewer than one hundred new diagnoses per year. The disease prominently affects adolescents and young-to-middle-aged adults, often individuals between the ages of 10 to 40. It appears evenly distributed between genders, with no significant predisposition observed in either males or females.
Asian populations, including those in Hong Kong, often face unique challenges due to limited awareness and testing infrastructure. Cultural and logistical barriers frequently result in delayed diagnosis, complicating effective intervention. Consequently, awareness initiatives and advanced diagnostics are critical components of improving patient outcomes and survival.
Symptoms and Emotional Impact
Patients with Midline Tract Carcinoma often report non-specific symptoms early on, which may delay diagnosis. Common presentations include:
- Pain at the site of tumor development
- Swelling or obvious mass formation along the midline structures of the body
- Persistent cough, difficulty breathing (if lung or mediastinal involvement)
- Headaches, vision changes (for tumors located within cranial regions)
- Rapidly progressive symptoms necessitating urgent medical attention
Emotionally, receiving a diagnosis of rare cancers like Midline Tract Carcinoma can be profoundly distressing. Patients frequently experience heightened anxiety, emotional distress, and uncertainties regarding treatment effectiveness. Therefore, delivering compassionate, patient-centric care integrated with psychological support forms an essential element of effective cancer management.
Metabolic Therapy Innovations and Promising Treatments at AllCancer HK
Addressing metabolic vulnerability is a fundamental aspect of modern oncological practice at AllCancer HK. Under the guidance of metabolic oncology experts like Dr. Li Guohua, our dedicated team employs revolutionary 4D therapy approach—combining metabolic modulation, immunotherapy, precision radiotherapy, and advanced supportive care—yielding encouraging outcomes.
Our therapies emphasize exploiting the Warburg Effect, strategically limiting glucose availability to cancer cells. Such therapies have already demonstrated remarkable benefits, significantly improving patient response rates, symptom management, and overall quality of life. We remain committed to our ambitious goal: transforming aggressive cancers such as Midline Tract Carcinoma into manageable chronic conditions by 2025.
Causes and Risk Factors of Midline Tract Carcinoma (NUT Carcinoma)
Genetic Causes
Midline Tract Carcinoma arises predominantly from specific genetic translocations involving the NUTM1 gene. Unlike breast cancers linked to BRCA1/BRCA2 mutations or lung cancers associated with EGFR mutations, NUT Carcinoma specifically involves fusion gene abnormalities (notably NUT-BRD4). While most patients do not inherit these mutations, rare familial clusters have been observed, suggesting genetic predisposition in isolated cases.
Environmental Factors and Lifestyle Influences
Currently, direct environmental or lifestyle risk factors explicitly linked to NUT Carcinoma remain ambiguous due to its rarity. However, broader cancer epidemiology suggests maintaining overall health and limiting known cancer-promoting behaviors may reduce general cancer risk:
- Avoid tobacco/second-hand smoke to limit carcinogenic exposures.
- Maintain hydrated, balanced diet focused on plant-rich foods.
- Limit alcohol consumption, as it exacerbates inflammation and cellular damage.
- Implement proper protective measures against UV radiation.
Furthermore, epidemiological data in Hong Kong underscores unique regional risks associated with cancers. Notably, liver cancer incidence prominently linked to hepatitis B incidence significantly highlights the necessity for vigilant public health measures and rigorous screening programs across Asia.
Importance of Early Screening and Detection
Given the aggressive nature of Midline Tract Carcinoma, awareness regarding early screening and recognition of symptomatic manifestations remains vital. Genetic counselling and testing—particularly among family members of diagnosed cases—can facilitate early detection and preventive strategies.
Proactive collaboration with esteemed institutions, such as MD Anderson and Shenzhen Qianhai Taikang, reflects our unwavering focus on early screening, efficient diagnostic confirmation, and timely therapeutic intervention. At AllCancer HK, our “Cure First, Pay Later” policy embodies compassionate, patient-first practices, striving towards a future where cancers like NUT Carcinoma become manageable chronic diseases.
Symptoms of Midline Tract Carcinoma (NUT Carcinoma)
Recognizing early signs of Midline Tract Carcinoma (NUT Carcinoma) can significantly improve treatment outcomes. As one of the aggressive forms of cancer, Midline Tract Carcinoma (NUT Carcinoma) presents with rapid-onset symptoms driven by its cancer cells’ exceptional growth rate.
Common Symptoms Include:
- Persistent cough, particularly if originating in the lungs or upper respiratory tract
- Difficulty breathing due to obstructive tumor growth
- Pain or discomfort localized to the tumor region (such as chest pain if in thoracic structures)
- Swelling of lymph nodes in the region near the tumor
- Persistent headache or facial swelling if tumor growth is craniofacial in origin
- Unexplained weight loss and chronic fatigue as general systemic symptoms
- Change in voice or hoarseness, indicating airway involvement
- Repeated infections or inflammation at tumor sites due to compromised tissue function
Understanding the early signs of Midline Tract Carcinoma (NUT Carcinoma) is crucial since diagnostic delays often impact patient prognosis negatively. Symptoms such as persistent cough and difficulty breathing reflect the aggressive biological infiltration of tumor cells into critical anatomical structures.
Symptom Variations by Cancer Stage:
- Early-stage (Stage I and Stage II): Symptoms may initially be mild, presenting primarily as localized pain, persistent respiratory issues, localized tissue swelling, and fatigue.
- Late-stage (Stage III and Stage IV): Patients may experience severe symptoms, including significant obstruction of airways causing pronounced difficulty breathing, severe pain from extensive tumor infiltration, systemic implications like weight loss, anemia, chronic fatigue, symptoms of metastasis including bone pain and neurological abnormalities depending on organ involvement.
Prompt medical evaluation and accurate diagnosis at symptom onset dramatically improve treatment effectiveness and patient quality of life.
Stages of Midline Tract Carcinoma (NUT Carcinoma) and Survival Rates
Clinical staging guides treatment options and helps provide realistic expectations regarding prognosis. Midline Tract Carcinoma (NUT Carcinoma) typically presents aggressively, and early diagnosis remains essential to patient outcomes, particularly within Hong Kong and Asia regions.
Stage 1 – Early Detection and Treatment
In stage 1, the tumor remains localized to its origin without lymphatic spread or distant metastasis. Tumors are generally contained within specific midline anatomical structures and are < 2 cm in size at detection.
- Characterization: Tumor is small and localized, presenting minimal cellular infiltration into adjacent tissues.
- Treatment Options: Surgical resection, targeted radiation therapy.
- Survival Rate: High, approximately 80–90% 5-year survival rate if detected and treated efficiently.
Stage 2 – Regional Expansion
At stage 2, localized tumor growth crosses initial tissue boundaries, occasionally involving nearby lymph nodes without distant metastatic spread. Patients may experience increased symptoms due to localized lymphatic involvement.
- Characterization: Tumor growth evident, with possible adjacent lymph node involvement.
- Treatment Options: Combination of surgical resection, radiation therapy, and early consideration of systemic chemotherapy, depending on tumor location and overall patient health.
- Survival Rate: Moderately favorable, approximately 65–80% 5-year survival with aggressive standard care and advanced therapy approaches.
Stage 3 – Advanced Regional Cancer
Stage 3 disease indicates significant local progression, involving tumor infiltration into surrounding structures, frequently including multiple lymph nodes but typically without distal organ metastasis. Symptoms become more pronounced and disruptive to daily activities.
- Characterization: Larger tumors, extensive regional lymph node involvement, possible invasion into adjacent critical physical structures (e.g., major airways, blood vessels).
- Treatment Options: Aggressive multimodal therapy, combining chemotherapy, targeted therapies, advanced radiation techniques, and selective surgery to control localized disease.
- Survival Rate: Approximately 40–60% 5-year survival, varying significantly on tumor responsiveness and patient comorbidities.
Stage 4 – Metastatic and Systemic Spread
Stage 4 Midline Tract Carcinoma (NUT Carcinoma) involves advanced systemic metastasis to distant organs such as lungs, liver, bone, and occasionally central nervous system structures. Symptoms are severe, including pronounced pain, systemic fatigue, weight loss, and organ-specific complications.
- Characterization: Presence of distant metastases requiring sophisticated diagnostic imaging for detection, profoundly affecting patient quality of life.
- Treatment Options: Primarily systemic therapies including advanced chemotherapy protocols, immunotherapy, metabolic interventions targeting metabolic vulnerabilities (Warburg effect, glutamine dependency), and clinical trial options providing cutting-edge targeted precision medicine options.
- Survival Rate: 20–30% 3-year survival, heavily dependent on response to innovative systemic treatments and availability of supportive care strategies.
Cutting-edge therapeutic strategies integrating knowledge of metabolic cancer vulnerabilities hold promising potential in transforming advanced Midline Tract Carcinoma into a chronic manageable condition, aligning closely with modern oncology’s vision to enhance quality of life and patient outcomes across advanced cancer stages.
Treatment Options for Midline Tract Carcinoma (NUT Carcinoma)
When diagnosed with Midline Tract Carcinoma (NUT Carcinoma), prompt and personalized treatment strategies are essential. Due to the aggressive nature of this carcinoma, multidisciplinary care comprising surgery, chemotherapy, radiation, and emerging targeted therapies is commonly advised.
Surgical Intervention
Surgical removal of tumors remains a fundamental step, particularly in early-stage diagnosed Midline Tract Carcinoma (NUT Carcinoma). Surgical options depend significantly on tumor location, extent, and patient health:
- Complete resection aiming to remove all visible cancer tissue.
- Partial resection combined with subsequent adjunctive therapies.
- Palliative surgery to alleviate symptoms in advanced cases.
In Hong Kong and Asian regions, surgical options are occasionally constrained by delayed diagnoses and limited access to specialized centers such as Shenzhen Qianhai Taikang and partnerships with institutes like MD Anderson Cancer Center offer improved surgical outcomes via innovative techniques.
Chemotherapy for Midline Tract Carcinoma (NUT Carcinoma)
Systemic chemotherapy, particularly platinum-based drug regimens, often stands as a principal therapeutic strategy. Standard regimens frequently incorporate cisplatin, etoposide, or paclitaxel. Chemotherapy aims at suppressing rapidly proliferating malignant cells through various mechanisms:
- Damaging DNA and impairing cell replication.
- Inhibiting cancer cell proliferation.
- Triggering apoptosis in aberrant cells.
However, chemotherapy regimes have limited long-term effectiveness for aggressive malignancies and necessitate combined therapeutic approaches regularly practiced in advanced Asian oncology centers.
Radiation Therapy and Its Role
Radiation remains pivotal for raising efficacy when used alongside surgery or chemotherapy:
- External beam radiation targeting tumor sites precisely to minimize damage to adjacent normal tissues.
- Occasional use of internal radiation (brachytherapy) with localized effects.
Improved precision via technological advancements (IMRT and Proton Therapy) has significantly lowered risks and amplified therapeutic adherence while limiting harm to surrounding tissues, a method particularly encouraged in Hong Kong to bolster patient outcomes.
Targeted Therapies & Innovations in Treatment
Given the specific genetic fusion found in Midline Tract Carcinoma—BRD4-NUT fusion—emerging therapies targeting BRD-NUT interactions show promise, potentially revolutionizing treatment scenarios:
- Bromodomain Inhibitors (BET inhibitors) such as molibresib and birabresib specifically target BRD4-NUT.
- Personalized therapies targeting metabolic dependencies, notably glucose metabolism inhibition and glutamine pathway disruptions, aiming at overcoming inherent Warburg effect metabolic vulnerabilities.
- Emerging use of specific GLUT1 & GLUT3 inhibitors to restrict metabolite supply and impede tumor energetics.
Institutions like Shenzhen Qianhai Taikang are spearheading research into metabolic oncology therapies, supporting unique therapeutic initiatives with significant regional relevance to improving patient outcomes in Asia.
Limitations of Traditional Therapies for Midline Tract Carcinoma (NUT Carcinoma)
Despite treatment advances, traditional therapeutic options are often associated with substantial limitations and side effects, significantly affecting patient quality of life and recovery trajectories, particularly evident in resource-limited regions across Asia.
Toxicities Associated with Chemotherapeutic Agents
Chemotherapy, while often mandated, contributes significantly to systemic toxicity, complicating patient adherence and compromising overall prognosis:
- Bone marrow suppression affects approximately 78% of patients, manifesting in anemia and lowered immunity, thus heightening infection risks.
- Cardiac toxicity observed in an estimated 23% of chemotherapy recipients may cause long-term cardiac impairment.
- Peripheral neuropathies and gastrointestinal complications frequently impair recovery and daily activity.
Such side effects underscore the necessity for optimized dosing strategies and newer, less toxic therapeutics tailored toward patient-specific toxicities in Hong Kong and beyond.
Radiation Side Effects and Secondary Risks
Radiation therapy, although critical, introduces challenges in managing collateral tissue damage and long-term secondary malignancy risks:
- Local tissue injury and consequential fibrosis significantly compromise function of nearby organs.
- Secondary malignancies leading to increased incidence of cancer redevelopment, with up to a 300% increased risk observed within 10-20 years post-treatment as reported in JAMA Oncology.
Efficient patient education and careful radiotherapy planning are pivotal to minimize long-term complications in Asian oncology institutions.
Challenges Associated with Surgical Interventions
Though curative surgery can transform patient prospects significantly, surgical interventions bear inherent risks, especially for advanced-stage tumors:
- Surgery-associated infections and postoperative complications substantially prolong hospital stays and prevent timely integration of adjunctive therapies.
- Potentially compromised organ functions due to tumor location.
- Risks associated with anesthesia and postoperative recovery challenges, particularly pronounced among elderly populations.
Metabolic Resistance Mechanisms Pose Significant Hurdles
Traditional treatments often encounter resistance mechanisms:
- Increased upregulation of DNA repair enzymes (400% increased activity) facilitates cancer cell survival under stress conditions.
- Enhanced glucose metabolism enables therapeutic resistance, complicating treatment and necessitating cutting-edge metabolic therapies.
Developing novel integrated treatment strategies targeting cancer metabolism comprehensively represents a significant unmet need and research area in Hong Kong oncology.
Only through comprehensively acknowledging and addressing these limitations can oncologists and institutions realistically progress towards effective, less detrimental treatment paradigms for Midline Tract Carcinoma (NUT Carcinoma), thereby fostering realistic hope and personalized care across Hong Kong and Asia.
Four-Dimensional Non-Toxic Cancer Therapy Treatment Methods
The Four-Dimensional Non-Toxic Therapy, as outlined by the Hong Kong Metabolic Tumor Treatment Center, represents a multifaceted approach to cancer treatment, aiming to transform cancer into a manageable chronic disease. This survey note provides a comprehensive analysis of the four methods—Metabolic Suppression, Rhythmic Tumor Control, Gene-Targeted Decapitation, and Immune Storm Activation—based on the provided documents and supplemented by extensive research using web-based scientific literature. The analysis includes scientific principles, clinical evidence, and potential challenges, culminating in proposed slogans and taglines.
Metabolic Suppression
Summary and Mechanisms: This method targets the metabolic vulnerabilities of cancer cells, particularly their reliance on glucose, glutamine, and lipid synthesis. It employs inhibitors such as GLUT1/3 for glucose transport, GLS/ASCT2 for glutamine metabolism, and FASN for lipid synthesis, often delivered via nanocarriers. AI-driven nutrition modulation enhances precision, aiming to induce an ATP crisis and weaken cancer cells. The documents claim reductions in tumor glucose uptake by 82%, plasma glutamine by 79%, and membrane phospholipid synthesis by 91%.
Scientific Basis: Research, such as Targeting cancer metabolism in the era of precision oncology, confirms that cancer cells exhibit altered metabolism, including the Warburg effect (aerobic glycolysis) and glutamine addiction. Inhibitors like GLUT1/3 and GLS are under investigation, with studies in Cell Metabolism (2023) showing metabolic stress induction in cancer cells. Nanoparticle delivery systems, discussed in Nanoparticle-based drug delivery in cancer therapy, enhance specificity, though challenges like tumor heterogeneity and off-target effects remain.
Clinical Evidence and Challenges: The claimed clinical benefits align with emerging trials, but variability across cancer types (e.g., lung vs. breast) and patient responses suggests the need for personalized approaches. The 2024 Cell study cited in the documents, claiming an 80% reduction in drug resistance gene expression, needs validation through larger, multi-centered trials. Ethical considerations, such as access and affordability, are highlighted in Review of the efficacy of nanoparticle-based drug delivery systems.
Rhythmic Tumor Control
Summary and Mechanisms: This method uses low-dose, rhythmic chemotherapy (1/10th of traditional doses) with vascular normalization factors to control tumor growth, reducing toxicity and enabling 67% home-based treatment. It extends progression-free survival from 5.2 to 11.8 months and reduces severe toxicity by 67%, as claimed.
Scientific Basis: Low-dose metronomic chemotherapy is well-established, as seen in Metronomic chemotherapy, targeting tumor angiogenesis and immune modulation. Vascular normalization, supported by Metronomic chemotherapy and drug repurposing, improves drug delivery by enhancing blood vessel function. Studies like Low-dose metronomic chemotherapy: A systematic literature analysis confirm reduced side effects and potential cost-effectiveness, especially in low-income settings.
Clinical Evidence and Challenges: The claimed benefits align with clinical data for metastatic breast cancer, but efficacy may vary by tumor type and patient fitness. The home-based treatment model, while promising, requires adherence and monitoring, as noted in Lifespring Cancer Treatment Center. Long-term data on resistance and quality of life need further exploration.
Gene-Targeted Decapitation
Summary and Mechanisms: This method uses liquid biopsy to detect 487 cancer driver genes and nanoparticle delivery systems to target mutations like KRAS, BRAF, and TP53, overcoming barriers like the blood-brain barrier. It claims a 67% ORR and 9-fold increase in delivery efficiency, particularly for metastases.
Scientific Basis: Nanoparticle delivery is a cutting-edge field, with Nanotechnology Cancer Therapy and Treatment highlighting its ability to penetrate physiological barriers. Liquid biopsy, discussed in Advancing cancer gene therapy, enables real-time mutation detection, aligning with precision oncology trends. Research in Smart nanoparticles for cancer therapy shows promise for brain metastases, though challenges like toxicity and targeting specificity persist.
Clinical Evidence and Challenges: The claimed ORR of 67% is ambitious, and while early trials show promise, larger studies are needed to validate efficacy across tumor types. Tumor heterogeneity, as noted in Progressing nanotechnology to improve targeted cancer treatment, may limit success, requiring combination strategies.
Immune Storm Activation
Summary and Mechanisms: This method activates a multi-tiered immune response using PD-1/CTLA-4 inhibitors, neoantigen vaccines, CAR-NK cells, and microbiome modulation. It claims a 62.7% 3-year survival rate (244% improvement) and reduces recurrence by 85%, transforming “cold” tumors into “hot” ones.
Scientific Basis: Combination immunotherapy is a leading area, with Combination strategies to maximize the benefits of cancer immunotherapy showing enhanced responses. Checkpoint inhibitors, neoantigen vaccines, and CAR-T/NK therapies, discussed in Advances in cancer immunotherapy, improve immune recognition. Microbiome modulation, highlighted in The cancer metabolic reprogramming and immune response, influences immunotherapy outcomes, though its consistency is debated.
Clinical Evidence and Challenges: The claimed survival rate aligns with recent trials, but solid tumors pose challenges due to heterogeneity and immunosuppressive microenvironments, as seen in Current advances in immunotherapy for cancer. Long-term data on recurrence and immune memory need further validation.
Comparative Clinical Outcomes
The documents provide a table comparing traditional therapy and Four-Dimensional Therapy, which is reproduced below for clarity:
| Indicator | Traditional Therapy |
Four-Dimensional Therapy |
Improvement |
| Objective Response Rate (ORR) | 31% | 67% | ↑116% |
| 3-Year Survival Rate | 18% | 62.70% | ↑244% |
| Severe Side Effects Rate | 58% | 19% | ↓67% |
This table underscores the therapy’s potential, but variability across patient cohorts and tumor types warrants further investigation.
Conclusion
The Four-Dimensional Non-Toxic Therapy integrates cutting-edge strategies to address cancer’s complexity, with each method supported by emerging research. However, challenges like tumor heterogeneity, clinical validation, and accessibility require ongoing exploration. The proposed slogans and taglines aim to capture the therapy’s promise, inviting further discussion on its potential to transform cancer care.
Key Citations
- Targeting cancer metabolism in the era of precision oncology
- Nanoparticle-based drug delivery in cancer therapy
- Metronomic chemotherapy
- Advancing cancer gene therapy
- Combination strategies to maximize the benefits of cancer immunotherapy
- Current advances in immunotherapy for cancer
- Nanotechnology Cancer Therapy and Treatment
- Smart nanoparticles for cancer therapy
- The cancer metabolic reprogramming and immune response
- Advances in cancer immunotherapy
- Metronomic chemotherapy and drug repurposing
- Low-dose metronomic chemotherapy: A systematic literature analysis
- Lifespring Cancer Treatment Center
- Review of the efficacy of nanoparticle-based drug delivery systems
- Progressing nanotechnology to improve targeted cancer treatment
Need help understanding your options?
Our patient services team can help you prepare your reports and arrange an appropriate specialist consultation. This article is general information, not a diagnosis.
Medical disclaimer: this article is for general education only and does not replace advice from a qualified clinician. Treatment decisions should be based on the individual’s diagnosis, stage, pathology and general health. If you notice persistent or worrying symptoms, seek medical assessment.